After triple therapy started at 72 hours, 8 infant macaques remained aviraemic for 6 months off treatment
In orally SHIV-infected infant macaques given LRM, bNAbs and 27 weeks of ART starting at 72 hours, all 8 animals were aviraemic 6 months after ATI with no CAVL detected in PBMCs or tissues.
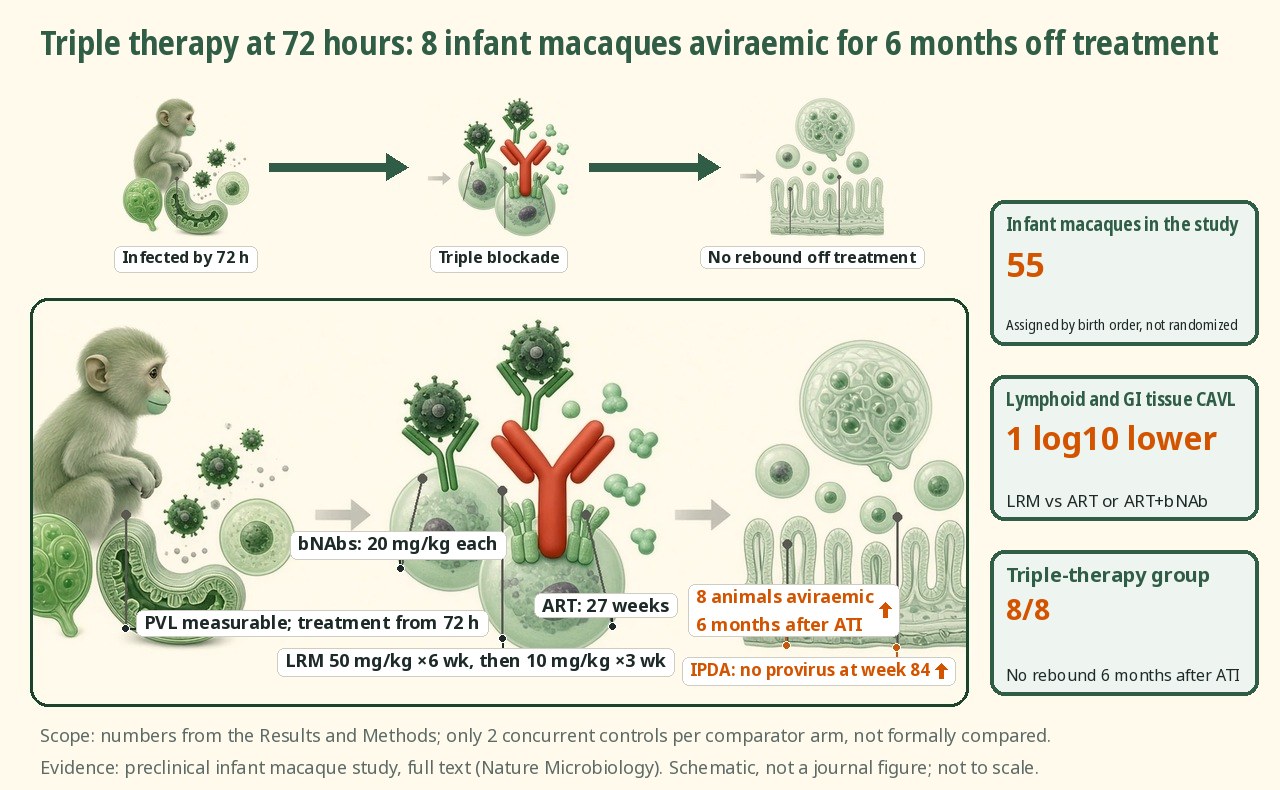
Fifty-five infant rhesus macaques around 4 weeks old were infected orally with a chimeric immunodeficiency virus and, at 72 hours, started the CCR5-blocking antibody leronlimab (50 mg/kg weekly), two broadly neutralizing antibodies, VRC07-523LS and PGT121 (20 mg/kg each), and 27 weeks of antiretroviral therapy. All 8 animals in the triple-therapy group were aviraemic 6 months after treatment interruption, with no cell-associated virus detected in blood cells or tissues and no provirus detected at week 84. Antibodies alone or antiretroviral therapy alone did not prevent reservoir seeding.
Background and open questions
After perinatal HIV acquisition in children, the latent reservoir remains hard to clear even when ART suppresses replication long term; mortality among untreated children can reach 50% within the first year. Existing data show that virus disseminates quickly in infant macaques after oral SIV or SHIV infection, and that ART started only at 72 h usually still allows rebound after treatment interruption.
bNAbs can neutralize Env and briefly lower viraemia, and the CCR5 antibody LRM can block the major coreceptor; but single strategies struggle to clear virus once the reservoir is established. In Nature Microbiology, Sacha et al. move the question to 72 h after exposure, testing whether neutralization, replication suppression and CCR5 blockade together can reduce the seeding of new foci of infection.
Study design
The study enrolled 55 male and female infant rhesus macaques around 4 weeks old, 6–8 per group, infected orally with a high dose of SHIV SF162P3 on a single day. Treatment mostly began at 72 h, when plasma viraemia was already measurable. Animals were assigned to groups in order of birth date rather than randomized; pathology and viral quantification experiments were performed blinded on coded samples.
The triple-therapy group began LRM, bNAbs and ART at 72 h: LRM at 50 mg/kg weekly for 6 weeks then 10 mg/kg weekly for 3 weeks, PGT121 and VRC07-523LS at 20 mg/kg each as a single dose, and daily TDF/FTC/DTG ART for 27 weeks; ATI followed confirmation that bNAbs, LRM and CCR5 occupancy had washed out. The main infection readouts were PVL and PBMC CAVL, with sample sizes estimated for 80% power at alpha=0.05 to detect PVL differences; no data were excluded, and viral readouts were monitored longitudinally.
Key results
Defining the window
A single bNAb dose at 48 h cleared virus in 5/6 infants; delayed to 72 h, all 6 animals given bNAbs alone rebounded, 4 at weeks 5–6 and 2 at weeks 16 and 22. Starting 21 days of ART or ART+bNAb at 72 h left only 2/6 in each case below the limit of detection, showing that neutralization alone or short-course ART is insufficient at 72 h.
CCR5 blockade reduces dissemination
LRM monotherapy weekly for 28 weeks lowered steady-state plasma virus by 2–4 log10, with 3/6 undetectable at the end of treatment, yet all 6 still had cell-associated virus in PBMCs. LRM plus 27 weeks of ART also failed to prevent infection: 4/6 rebounded after ART withdrawal, 3 of them with plasma and PBMC virus delayed by 9–10 weeks.
Smaller tissue reservoirs
Necropsy tissues showed that LRM lowered lymphoid tissue CAVL by 1 log10 relative to ART or ART+bNAb; in gastrointestinal tissue, LRM alone or with ART also lowered it by 1 log10. The figure legends note that these tissue comparisons used two-way ANOVA with Tukey multiple comparisons, with significance marked from P<0.05 to P<0.0001.
No rebound after triple therapy
All 8 triple-treated infants remained aviraemic 6 months after ATI, with no CAVL detected in PBMCs or tissues in any animal. The 2 untreated controls in the same experiment had uncontrolled viraemia, and 1 was euthanized at week 20 for AIDS-related disease; the 2 ART+bNAb controls rebounded after ATI with peaks of 10^5 or 10^6 copies/ml and developed Gag-specific CD8 T cells and anti-Env antibodies, none of which appeared in the triple-therapy group.
No latent virus detected
At week 56, none of the 8 triple-treated infants had Gag-specific CD8 T cells or anti-Env antibodies; after CD8 cell depletion at week 61, none of the 8 showed rebound in plasma virus or cell-associated DNA, whereas surviving controls and the 2 ART+bNAb animals developed viraemia and detectable CAVL. At necropsy at week 84, none of the 8 triple-treated animals had a single sample positive for viral nucleic acid, and IPDA of lymphoid tissue CD4+ T cells detected no intact or defective provirus, while controls and ART+bNAb animals had viral DNA.
Mechanistic interpretation
Demonstrated in the paper: The demonstrated chain is as follows: plasma virus is already measurable at 72 h, and bNAbs, ART or LRM alone cannot clear all infection; LRM maintains CCR5 receptor occupancy on blood CD4+ T cells and lowers lymphoid and gastrointestinal tissue CAVL by 1 log10. With bNAbs and 27 weeks of ART added, no replicating or latent virus was detected in 8 animals at ATI, after CD8 depletion or at necropsy at week 84.
The immunological readouts support the view that control is not maintained by measurable adaptive antiviral immunity. At week 56, controls and the 2 ART+bNAb animals had measurable Gag-specific CD8 T cells, and the 2 ART+bNAb animals also had anti-Env antibodies; none of these responses was observed in the 8 triple-treated animals, and CD8 depletion did not provoke rebound.
Author hypotheses: The authors suggest that the triple effect may come from layered blockade: bNAbs neutralize Env, ART suppresses replication, and LRM blocks CCR5 entry and may alter trafficking of CCR5+CD4+ T cells to gastrointestinal tissue. The paper states explicitly, however, that the mechanism of synergy between LRM and bNAbs is unknown, and there is no direct evidence that bNAbs mediate clearance of already-infected cells.
Limitations and uncertainties
- Intervention at 72 h still precedes peak viraemia, a limitation the authors name explicitly; this approximates very early post-exposure treatment rather than infection diagnosed days later or chronic adult infection.
- The comparison groups in the triple-therapy experiment are very small: n=8 for triple therapy with only 2 untreated and 2 ART+bNAb concurrent comparators. The study did not randomize but assigned animals in order of birth date; although viral quantification and pathology were blinded, between-group conclusions should not be read as large-sample efficacy comparisons.
- The authors acknowledge that deeper sampling of non-lymphoid tissues such as bone marrow or the central nervous system might still reveal latent virus; the study focused sampling on lymphoid tissue, PBMCs, gastrointestinal tissue and spleen. No detection at week 84 is not equivalent to proving absolute absence of virus at every anatomical site.
- The mechanism remains open: if CCR5 blockade depends mainly on coreceptor occlusion, it may not apply to transmitted viruses using CXCR4; the mechanism of synergy between LRM and bNAbs is unknown, and efficacy in adult HIV infection has not been tested.
Clinical and industry implications
If this infant macaque model predicts human perinatal infection, combining bNAbs, ART and CCR5 blockade within 72 h could shift the therapeutic goal from long-term suppression to preventing a permanent reservoir from maturing. Its translational appeal is that LRM, VRC07-523LS and PGT121 are all human antibodies or products relevant to clinical research.
Industrial and clinical progress should nonetheless presuppose early identification of exposure, accessible dosing and viral tropism. The study supports designing intensified post-exposure regimens for newborns but should not be read as showing that paediatric HIV is now curable; the key next steps are to test different exposure doses, start times and CXCR4-related risk.
Numbers are as reported by the authors. Corrections: contact@
Related science
44% of rhesus macaques developed serum bnAb activity after the complete sequential HIV vaccine regimen
Three generations of B cells maturing step by step, with antibodies binding the viral spike at right

Observational study: mRNA-1010 recipients had larger increases in memory B cells
A cross-section of a lymph node germinal centre, with memory B cells at right
A fungal glycan adjuvant extends COVID-19 mRNA vaccine protection to day 500
Lipid particles with mannan chains, a dendritic cell and a B cell producing antibodies
One email, with links to every paper. Reports and custom landscapes: contact@inlightbio.com.
Opens your email app with a pre-filled request; we add you by hand. Free, unsubscribe any time.